
Dissection by Lars Poulsgaard, MD
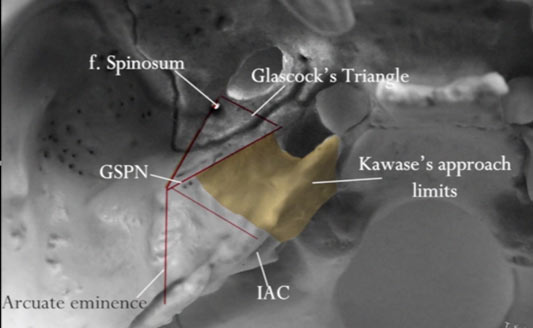

The anterior petrosectomy technique is used to reach lesions in the upper clival area (not below the internal acoustic canal). The inferior border of petrous apex drilling is the inferior petrosal sinus.
Case presentation and indication
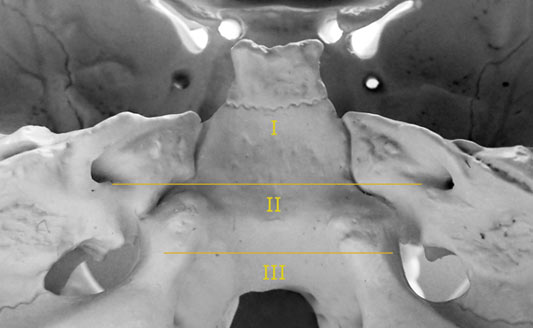
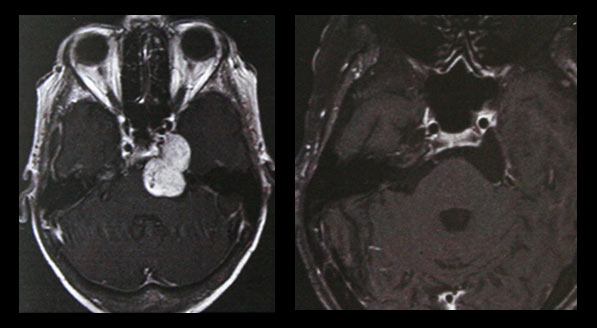

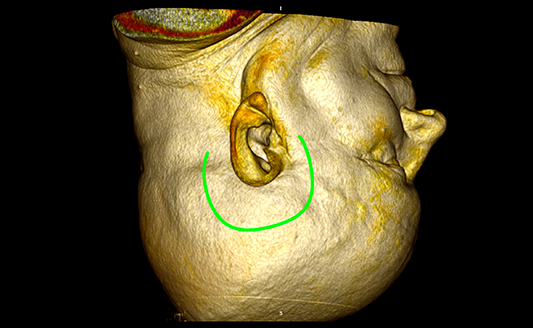
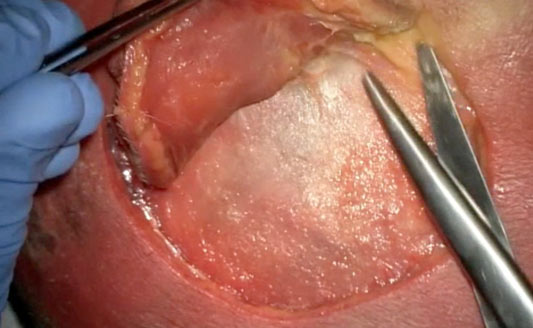
Fig. 1 and 2. Skin incision and development of skin flap
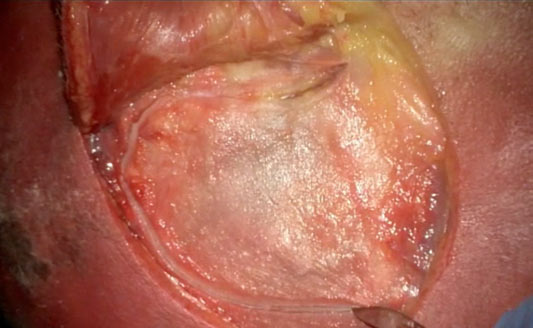
Fig. 3. The muscle flap is elevated towards the muscle's feeding vessels from deep temporal artery.
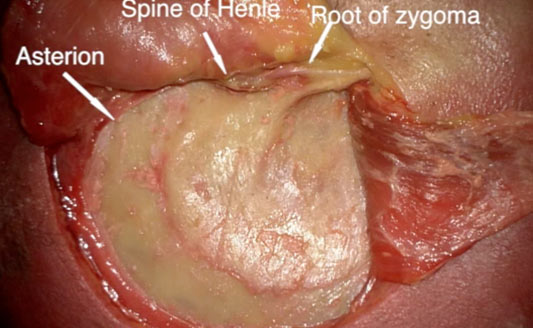
Fig. 4. Bone anatomy
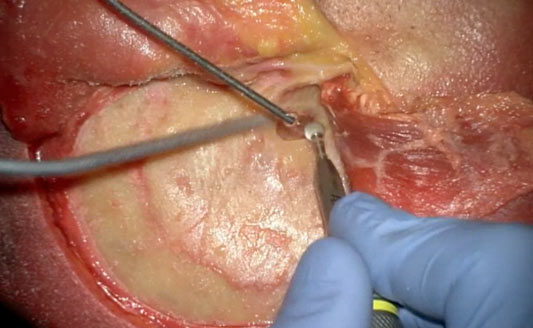
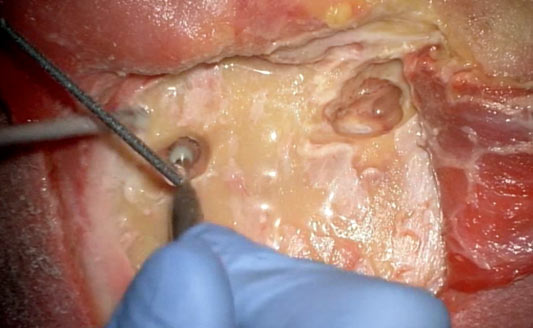
Fig. 5. Burr holes placement
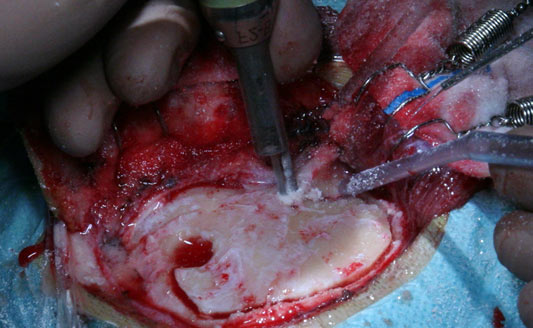
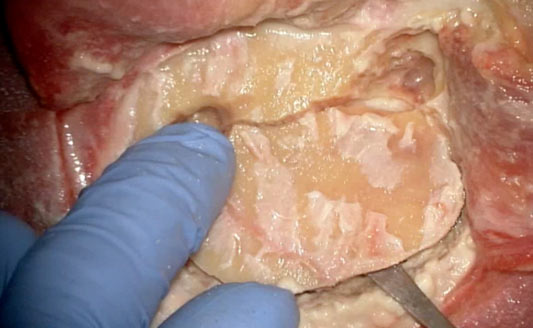
Fig. 6. Craniotmomy
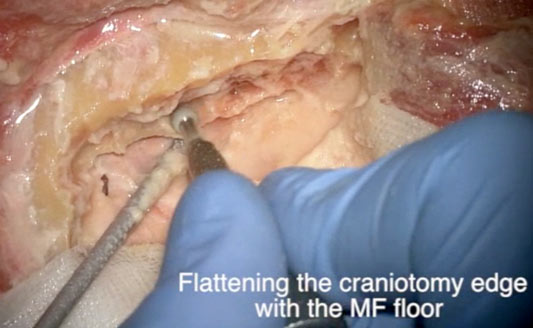
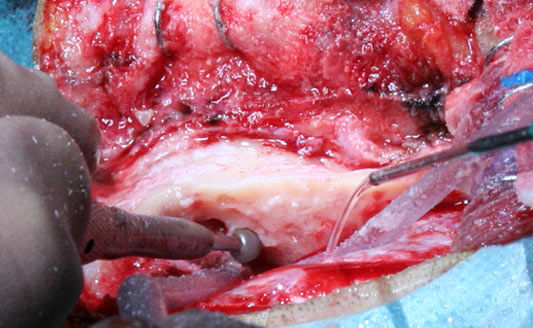
Fig. 7. Flattening the craniotomy edges with the middle fossa floor.
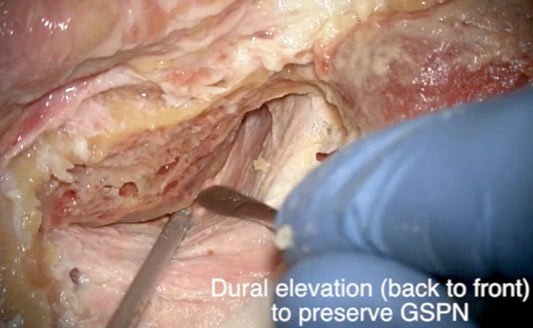
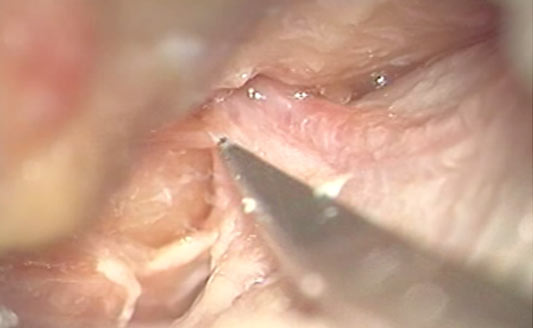
Fig. 8 and 9.
The tip of the scissors are pointing to a branch to the facial nerve which should be preserved.
The dura is elevated from back to front manner in order to preserve the GSPN.
High magnification view of foramen spinosum and the middle meningeal artery.
The tip of the scissors are pointing a branch to the facial nerve which should be preserved.
The tip of the scissors are pointing to a branch to the facial nerve which should be preserved.
The dura is elevated from back to front manner in order to preserve the GSPN.
High magnification view of foramen spinosum and the middle meningeal artery.
The tip of the scissors are pointing a branch to the facial nerve which should be preserved.
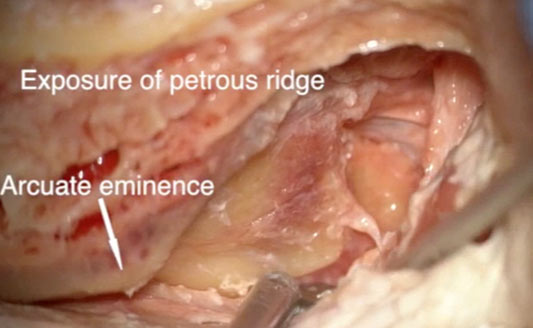
Fig. 10. Exposure of the petrous ridge.
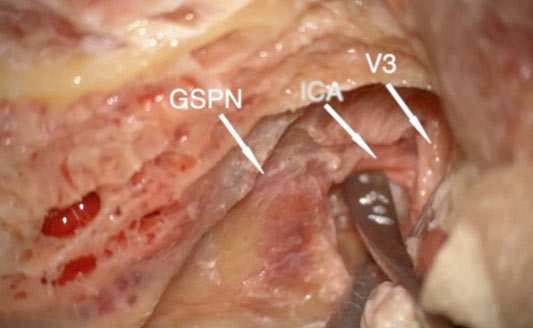
Fig. 11. Relevant anatomy
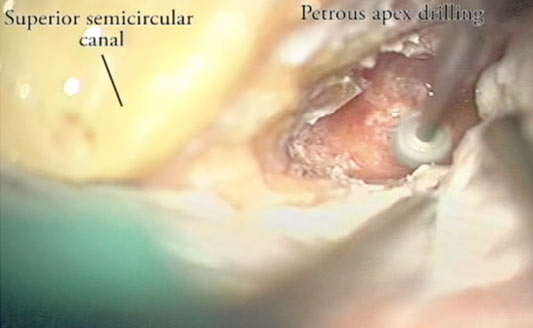
Fig. 12. The petrous apex is within in the boundaries described in the anterior petrosectomy chapter of the manual.
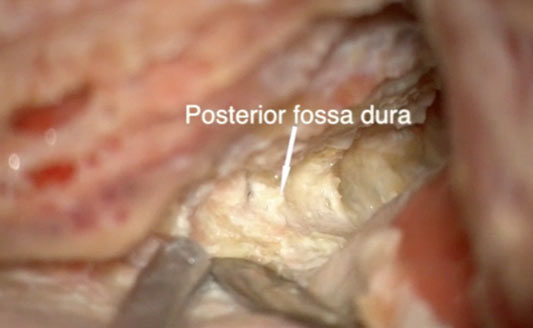
Fig. 13. The posterior fossa dura is exposed
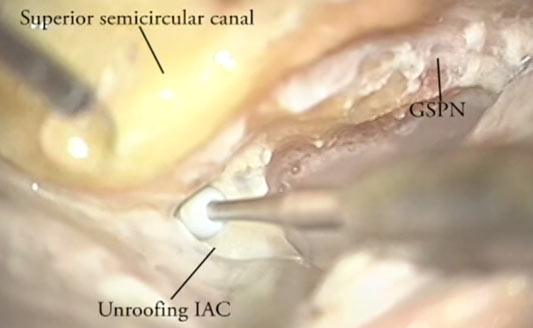
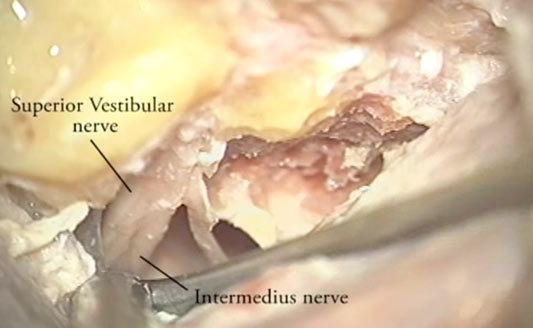
Fig. 14 and 15. The IAC is unroofed and the nerves in the internal acoustic meatus are presented.
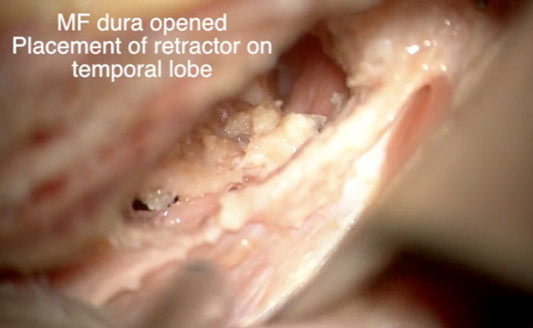
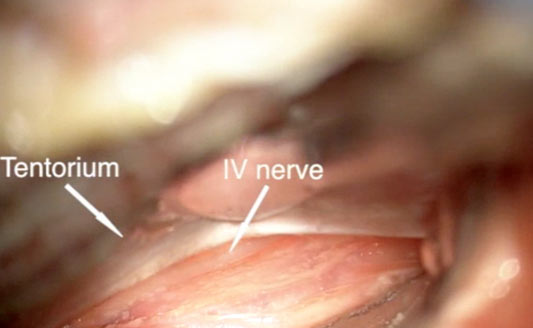
Fig. 16 and 17.
Middle Fossa dura is opened and a retractor is placed along the inferior surface of the temporal lobe. Tentorium is lifted in order to expose the IV nerve
Middle Fossa dura is opened and a retractor is placed along the inferior surface of the temporal lobe. Tentorium is lifted in order to expose the IV nerve
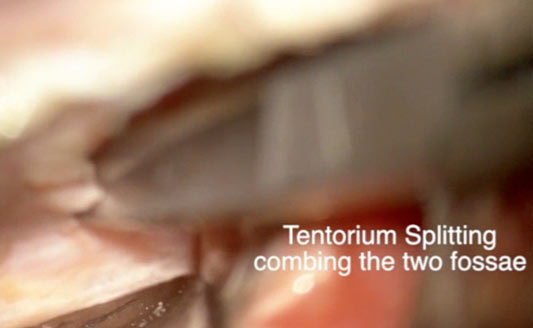
Fig. 18. Splitting the tentorim and combining the two Middle fossa and Posterior fossa.
The IV nerve must be avoided at the tentorium edge.
The IV nerve must be avoided at the tentorium edge.
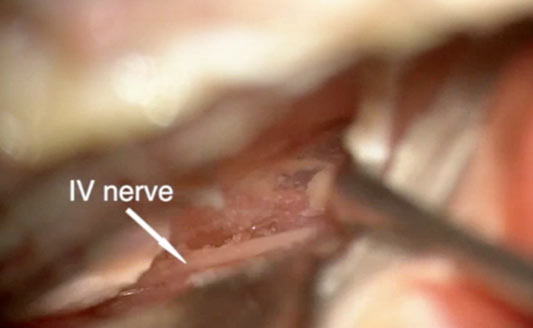
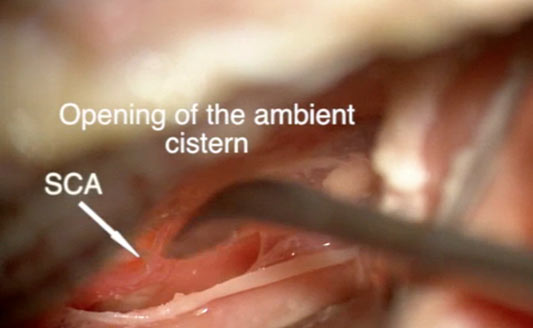
Fig. 19 and 20.
The IV nereve is seen and the ambien cistern with SCA are exposed
The IV nereve is seen and the ambien cistern with SCA are exposed
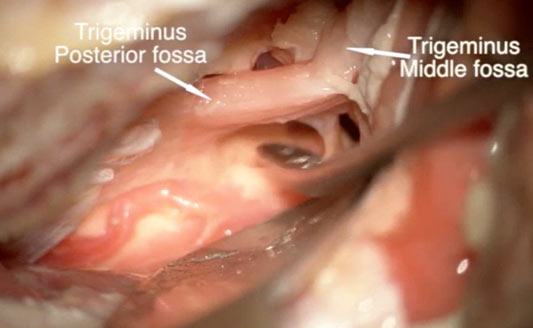
Fig. 21. The trigeminal nerve from its exit point from the pons and entering in the middle fossa is presented
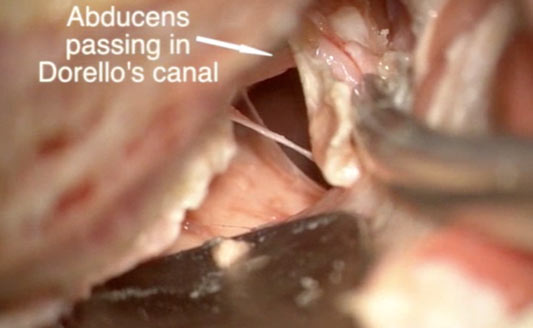
Fig. 22. The abducens nerve entering in the dorello’s canal is presented
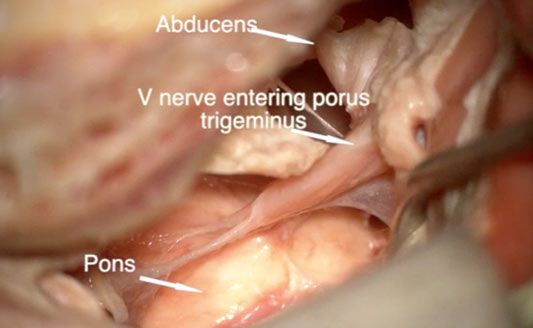
Fig. 23. Relevant anatomy
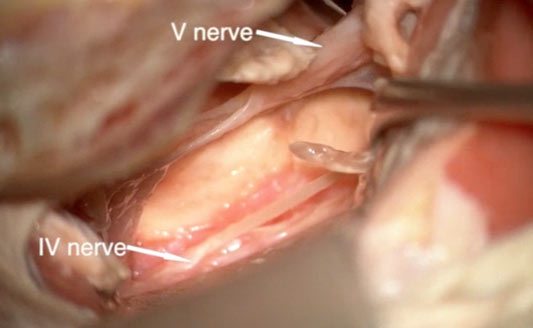
Fig. 24. Final view
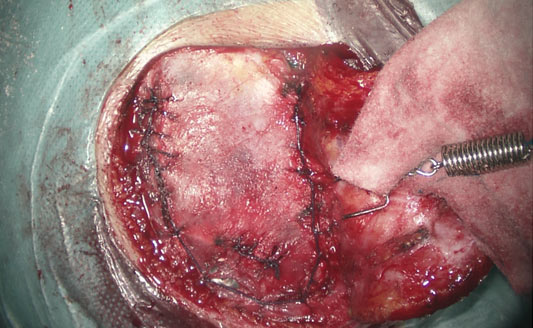
Fig. 25. Muscle closure in watertight fashion