10. SURGICAL TREATMENT OF EPILEPSY
Surgical treatment of epilepsy is applied in patients with inadequate control of epileptic seizures by medication i.e. it does not decrease the severity and frequency of the epileptic seizures, and they considerably disable the patient and stop him or her from leading a normal or nearly normal life. No strict rules dictate how many seizures constitute unacceptable control; this must be considered within the patient's vocational, social, and rehabilitation capabilities. For example, three epileptic attacks monthly may be insignificant to a patient who is severely mentally retarded. In contrast, the same number of seizures may be unacceptable for a 14-year old patient with normal intelligence and psychosocial potential. When the seizures are severe with a real danger of injury and the tendency to epileptic status or fast development of mental disturbances, operative treatment can be considered in the event of less frequent seizures and earlier progression.
Special attention must be paid to temporal lobe epilepsy, as it is favourably influenced by surgical treatment and is more resistant to medication than are the other forms of epilepsy. If drugs obviously have no effect, an early operation is recommendable, as it will allow normal education and social adaptation. On the other hand, in children, the attacks change with the maturation of the brain, so that it is very important to know with certainty that the tendency to have seizures is stable, before considering the indications for operation. In children with temporal lobe epilepsy it is better to let them become 15 - 16 years of age, when there is greater certainty that the epileptic focus has clearly been formed. On the other hand, 5 - 10% of patients with temporal lobe epilepsy, obtain spontaneous relief of seizures after 10 - 15 years of age.
The surgical treatment of epilepsy is pathogenic in principle and the etiology has just additional significance for improvement after the operation. However, in some clinical forms of epilepsy the etiology plays a certain role in the selection of patients for operation and is one of the criteria, which must be considered. Among the epilepsies with different etiologies, posttraumatic epilepsy is most favourably influenced by surgical treatment when compared with the others.
EVALUATION OF EPILEPTIC PATIENTS FOR SURGERY
A careful history is necessary, especially regarding evidence of birth trauma, seizures in early life, and other potential causes of epilepsy. Whether other members of the family have epilepsy should be ascertained. The clinical characteristic of epileptic attacks should be known in detail through questioning not only the patients, but also observers because more clinical details of seizures can be obtained from them. Phenomena such as transient dysphasia or postictal paresis or other transient deficits are of considerable value for lateralizing the epileptic focus.
A meticulous neurological examination is required and it may be normal or show deficit from minimal to marked.
Electrophysiological studies are essential for evaluating the patient for surgical treatment.
They can be divided into interictal and ictal recordings performed either extracranially or intracranially. The use of interictal recordings is not recommended for making any major surgical decision in selecting candidates for surgery. However, if interictal epileptic electrographic findings remain consistently restricted to one region of the cortex, like the temporal lobe for a period of years this region most likely harbours the epileptic focus.
Because interictal recordings have high error rate for localizing epileptic foci, long-term EEG monitoring has been used to provide ictal recordings to show the cerebral region of seizure's onset. These recordings can be taken from the scalp or intracranially. The combination of long-term scalp recordings with a video recording of the patient can provide important evidence of the seizure type that characterizes the patient's epilepsy.
Several methods for long-term interictal recordings are available and include deep electrodes, strip electrodes and grid electrodes. Foramen ovale electrodes are also an option.
An intracarotid amytal test to determining speech laterality can be used to select which cortical areas should remain unaffected in operated patients.
Metabolic and blood flow imaging (single photon emission computed tomography and positron emission tomography) have been also considered in the presurgical evaluation, demonstrating high values with ictal phenomena.
Most significantly CT and MRI can provide information for different structural lesions of the brain, because most focal types of epilepsy results from damage or abnormal development in the cortex and some deep structures, as in cortical dysplasia and hyppocampal sclerosis.
ANAESTHESIA
Local anaesthesia is preferable as it allows the establishment of constant contact with the patient during the electrostimulation of the brain cortex. In order to avoid pain at the time of the opening of the dura, local anaesthetic can be injected directly between its two layers by means of a fine needle in the places where the big branches of the middle meningeal artery are located. After the electrostimulation and the electrocorticography have been done, the operation can continue with general anaesthesia. In children and adults patients with mental disorders it is better to perform the operation under general anaesthesia and to decrease the depth of the latter at the time of the electrostimulation.
CORTICAL EXCISION
The patient can be placed on the operating table in different positions, depending on the location of the epileptic focus. However it should always be remembered that the face and the limbs must be free for observation, if a motor response is obtained during the stimulation of the brain cortex.
The extension of the scalp and bone flaps are determined depending of the epileptic focus, for which a topographic map must always be made. This map, made on the patient's head, is exact enough to locate the Sylvian and central fissures at least. Depending on these, the main circumvolutions on the convexity surface of the brain are also found. A wide craniotomy is necessary in order to reveal the epileptic focus and the neighboring regions of the cortex, depending on the clinical, electroencephalographic, CT and MRI data. In the presence of a bone defect situated over the cortex after trauma, after forming the scalp flap, the periosteum is released from the edges of the defect and a separation of the scar tissue from the dura is made. The scars of the dura are excised. If bone enostosis is discovered, the latter is also resected.
The dura is opened in the conventional way, but in cases of traumatic epilepsy, this may prove difficult, owing to its adhesions to the brain tissue. If these adhesions are very dense and are situated in a region, where their separation will induce brain injury and may evoke neurological deficit, it is better to make an electrostimulation and electrocorticography over the dura. When there are obvious morphological changes on the brain cortex, the epileptic focus is usually found in their neighbourhood. Sometimes cysts or scar tissue are revealed in the subarachnoid space in the depth of the brain sulci or brain tissue. At other times deeply situated foreign bodies are located surrounded by fibrosis.
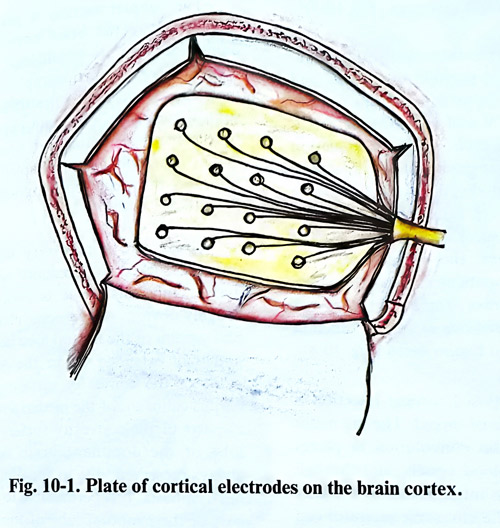
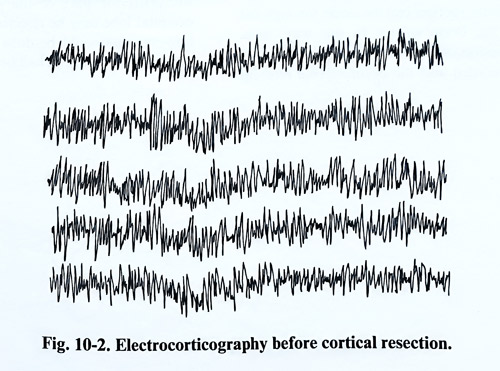
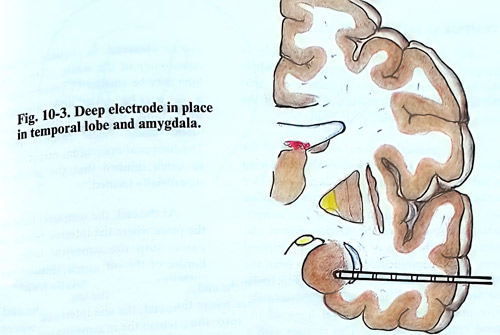
After this the electrocorticography continues as planned. We use contact cortical electrodes mounted on a rubber plate that can record from the exposed cortex of the craniotomy (Fig. 10-1; 10 - 2). They can also be introduced into the subdural space under the border of craniotomy, including on the basal surface of the brain hemisphere. After the electrocorticography study deep electrodes can also be used, especially those directed to the hippocampus and amygdala (Fig. 10-3).
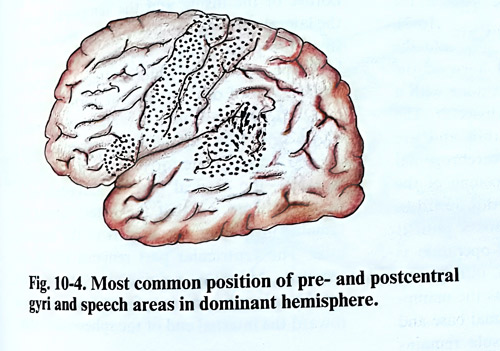
The brain cortex is then electrically stimulated to determine the position of the pre- and postcentral gyri. A 2 m/sec square-wave pulse at 60 Hz, starting at 1 V and increasing by 0.5 V increments following each negative stimulation is used until a motor response is seen, or until a sensory change is felt by the patient. Positive stimulation points are marked. The central sulcus (Rolandic fissure) is identified. In the dominant hemisphere, the speech areas are stimulated while the patient carries out simple verbal tasks. A negative stimulation does not always exclude the presence of speech function in the convolution that is stimulated (Fig. 10-4).
The area of proposed cortical resection is outlined and marked. The pia mater is incised on the brain convolutions in places where there are no blood vessels, and through the incision the suction tip is introduced into the gray matter of the brain. The ultrasonic aspirator can be used for tissue removal. The tissue is aspirated until white matter is reached without penetrating into the depth of the brain sulci. Using optic magnification, the penetration into the brain cortex and its suction can be made through the depth of the brain sulcus. In this way massuve adhesion of the brain tissue to the dura is avoided and the brain surface remains covered by pia-arachnoid.
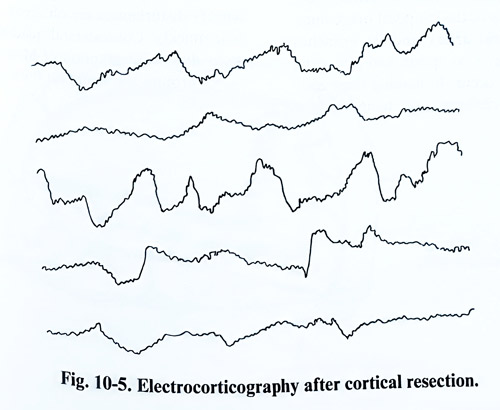
The subpial suction is performed in the regions where the brain cortex is obviously damaged, not relying essentially to electrocorticography and electrostimulation. In a case of posttraumatic epilepsy, subpial suction of the brain cortex is preceded by the removal of the scar tissue and foreign bodies if present. After completing the cortical resection, electrocorticography is repeated (Fig. 10-5).
Great care is necessary when the cortex must be aspirated in proximity with the central gyrus. There is removed only the tissue, which has obvious macroscopic changes. The subpial suction in the frontal lobe is most common, and may extend up to the anterior central gyrus of the convexity surface and up to the corpus callosum of the medial surface. The lower parts of the convexity surface of the frontal lobe of the dominant brain hemisphere are always preserved, due to the danger of provoking dysphasia. It is permissible to remove a large part of the temporal lobe of the non-dominant hemisphere. However, the removal of the posterior half causes hemianopia and this must therefore be preserved. It is permitted to resect the posterior part of the parietal lobe. The occipital lobe may be resected only on one side; however this could be done more freely if the patient has already hemianopia.
TEMPORAL LOBECTOMY
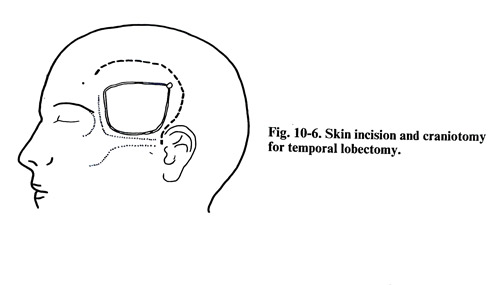
For the resection of the temporal lobe in temporal lobe epilepsy, a craniotomy is made in the frontotemporal region in such a way that the larger part of the convexity surface of the temporal lobe is exposed (Fig. 10-6).
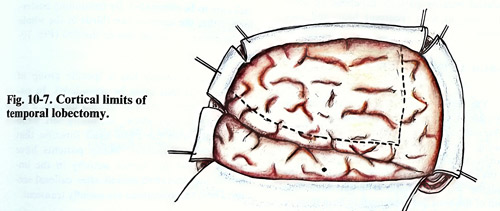
After opening the dura, identification of the Sylvian fissure is easy, as the lesser wing of the sphenoid is indicating its beginning. Two incisions are marked after the electrostimulation and the electrocorticography. The first is horizontal and parallel to the Sylvian fissure and passes along the path of the superior temporal gyrus. The second incision starts 4 cm from the temporal pole and goes vertically (Fig.10-7).
The vertical incision is first deepened into the white matter until the temporal horn of the lateral ventricle is opened. This is done with a fine suction tip and a thin brain dissector. The blood vessels encountered are thin and are coagulated. The appearance of cerebrospinal fluid in the incision shows the opening of the ventricle. The incision is extended downward to the floor of the middle cranial fossa until it reaches the hippocampus. If the operation is performed under local anaesthesia, intravenous anaesthetic is added at this stage as the manipulation around the dura of the cranial base and the tentorium is painful. The insula remains uncovered in its anterior-inferior surface, covered only by the pia of the temporal operculum.
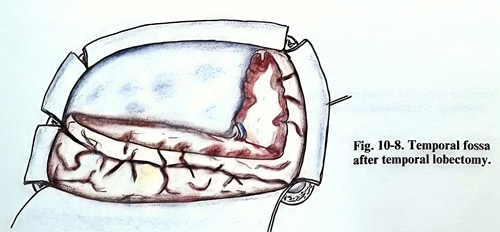
The middle cerebral artery and its branches should not be injured, as spasm and ischaemic complications may occur. In making these incisions, pathological changes in the temporal lobe can be observed, as cortical atrophy or denser consistency of the white matter. The temporal lobe may be smaller in volume and the Sylvian fissure may be located under the sphenoid ridge, which must be carefully observed, as important blood vessels, which are in it, may be injured. The temporal operculum might be atrophic and so much thinned that the insula may appear superficially located. At the end, the temporal lobe stem is cut at the place where the inferior border of the insula passes into the temporal lobe, between the border of the insula and the temporal horn of the lateral ventricle (Fig. 10-8). The section starts from the place, where the temporal horn has been opened and the white matter is interrupted under the roof of the temporal horn, bearing in mind the place where the choroid plexus is attached. In this way the entire temporal horn is opened postero-anteriorly, and before its anterior end, the cortical part of amygdala is exposed and cut, so that the antero-lateral half remains in the amputated part of the temporal lobe. After this manipulation, the incision reaches the pia mater of the temporal pole toward the internal end of the sphenoidal ridge.
As postoperative complications, motor and sensory disturbances are observed, which disappear quickly. Contralateral quadrantopsia may occur due to interruption of Meyer's loop as it passes around the temporal horn of the lateral ventricle.
CALLOSAL SECTION (CALLOSOTOMY)
The role of callosal section in the management of patients with medically intractable epilepsy has been empirically defined. The objective of a corpus callosotomy is not to remove an epileptic focus. The candidates for this procedure do not have a clearly defined and resectable epileptic focus, and callosotomy is performed to prevent the propagation of seizures from one hemisphere to the other. Although the disconnection does not eliminate all seizures, it can prevent the generalized tonic or atonic episodes that are manifested as drop attacks. Controlling drop attacks is essential because patients experiencing them often present with recurrent head and face injuries.
SURGICAL TECHNIQUE
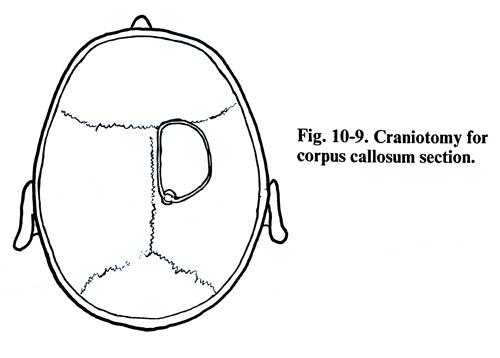
The patient is placed supine on the operating table. Using a U-shaped scalp flap on the right side, a frontal craniotomy is performed near to the midline (Fig. 10-9). The anterior margin of the craniotomy should be just in front of the coronal suture. After the position of the bridging veins is established in this area, one third of the bone flap is planned to be in front of the coronal suture and two thirds behind it.
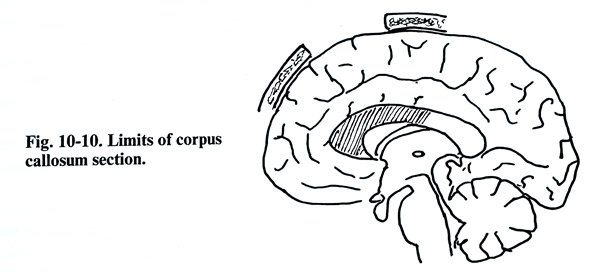
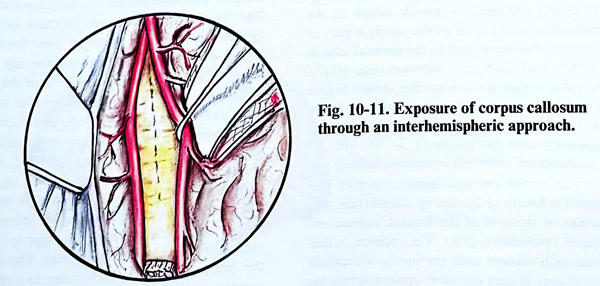
After opening the dura, the right hemisphere and the falx are retracted to expose the pericallosal arteries and the corpus callosum (Fig. 10-10). With bipolar coagulation and gentle suction of the corpus callosum, the ependymal lining of the lateral ventricle is reached, if possible, but not transgressed. The section is continued forward around the genu to divide down to the rostrum. The commissural fibers that link the supplementary motor areas cross in the rostrum and must be interrupted, if drop attacks are to be eliminated. By continuing posteriorly, either the anterior two thirds or the whole of the corpus callosum can be divided (Fig. 10-11).
The callosotomy has a specific group of complications that must be considered. In patients with relatively intact brain function, a set of symptoms may show, including left hand interference with the right hand function that usually slowly resolves. Many patients have reduced verbal and motor activity in the immediate postoperative period after callosal section. These complications are usually transient.
HEMISPHERECTOMY
Hemispherectomy is applied in patients who have sustained such major hemispherical damage that the hemisphere remains nonfunctional and epileptogenic. The seizures arise in the badly damaged cerebral hemisphere and cannot be adequately controlled by tolerable doses of appropriate medication. In most instances, the brain injuries have occurred in infancy or early childhood, resulting from perinatal trauma or from some inflammatory brain disease.
Two types of operation are known. The first is an anatomical hemispherectomy in which the entire brain hemisphere is resected, except the basal ganglia and thalamus. This operation leaves a large, empty space filled with CSF and carries the serious complication of progressive hemosiderosis. This type of hemispherectomy was replaced by the so-called functional hemispherectomy by removing the central cortex and the tip of the temporal lobe but leaving in place the frontal and occipital poles with bridging parietal cortex. These poles are disconnected from the remaining hemisphere by sectioning all the connections to the corpus callosum and basal ganglia.
SURGICAL TECHNIQUE
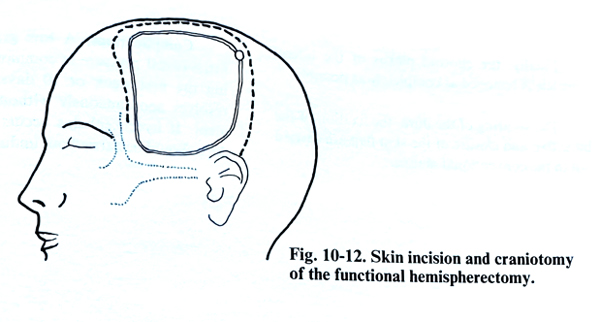
A large U-shaped scalp flap and large craniotomy are used to provide access to the frontal lobe at the level of the anterior part of the corpus callosum, and to the parietal lobe at a level behind the corpus callosum (Fig. 10-12).
The inferior part of the bone flap should expose the inferior aspect of the temporal lobe. After the dura is reflected an electrocorticography is obtained.
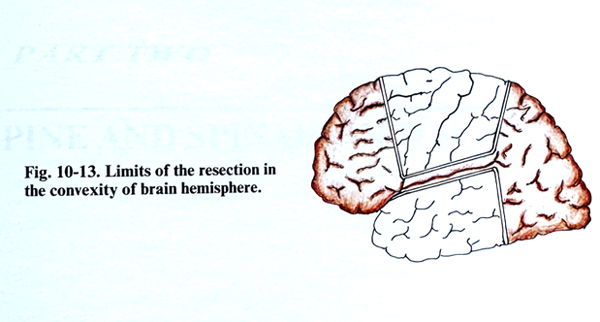
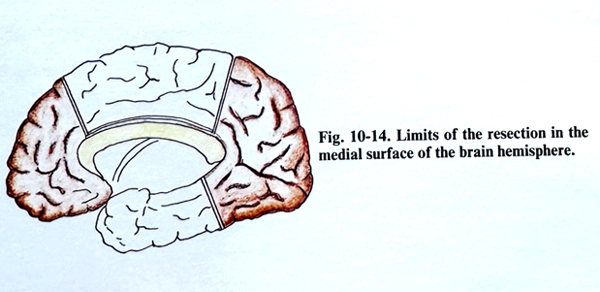
The initial cortical incision begins just above the fissure of Sylvius by coagulation, and incision of the gyri of the frontal, central and parietal opercular regions. The incision is deepened with suction until the insula is exposed. The incision is then extended upward across the frontal and parietal lobes to the midline (Fig. 10-13). The two vertical incisions are then extended on the medial surface of the hemisphere reaching the top of the cingulate gyrus. Leaving the cingulate gyrus in situ, the two vertical incisions are connected just above the cingulate gyrus. The posterior frontal, central, and anterior parietal brain tissue outlined by the cortical incisions is removed 'en bloc' by sectioning the underlying white matter with the suction tip.
The cingulate gyrus is then removed subpially with suction, exposing the anterior cerebral arteries covered by the leptomeninges (Fig. 10-14)
The frontal lobe is then disconnected completely from the upper brain stem and the corpus callosum by suction of white matter in front of the rostrum of the corpus callosum down to the leptomeningeal layer lying on the falx. The same disconnection of the parietal lobe is done by section of the white matter just behind the splenium of the corpus callosum down to the falx and tentorium.
The temporal lobe is completely removed back to the level of the parietal cortical incision.
The cortical incision is initially made just below the fissure of Sylvius and then deepened with suction down to the insula and around the tip of the temporal lobe to the uncus. The vertical incision goes downward to the temporal fossa.
The horizontal incision is then extended through the fusiform gyrus to meet the inferior aspect of the incision around the tip of the temporal pole. The temporal horn of the lateral ventricle is usually opened. After this stage of the operation the temporal lobe is disconnected from its stem and is removed, sectioning any remaining white matter by suction. The amygdaloid nucleus bulging in the medial aspect of the tip of the temporal horn of the ventricle is also removed.
The medial part of amygdala is preserved to protect against inadvertent damage to the hypothalamus and to the optic tract. The pes and the body of the hippocampus are removed completely with any remaining gray matter of the fusiform and hippocampal gyri. Finally, the choroid plexus of the lateral ventricle is removed as completely as possible.
The suturing of the dura, the fixation of the bone flap and closure of the skin flap are carried out in the conventional manner.
Complications. A low-grade increase of intracranial pressure is commonly present during the first week or 10 days, which usually resolves spontaneously without specific treatment. If hydrocephalus occurs a shunting procedure should be carried out without delay.